

Sterilising
Surfaces finished to 0.25–0.6µm Ra – well below the 0.8µm Ra hygienic-design benchmark
Validated
Measurable, repeatable processes – built for ISO 13485 and FDA QMSR (21 CFR 820) validation
Precise
Controlled media delivery reaches complex geometry without distortion
Clean
No embedded abrasive. No residual contamination. Surface ready for the next step.
The instruments that enter a patient's body carry no margin for error. A burr left on a scissor jaw. A surface too rough to sterilise reliably in an autoclave. A finish that varies between production batches and cannot be validated. These are not quality concerns. They are compliance failures and patient safety risks. Every one of them is traceable to how the instrument was finished.
Wet blasting (also called vapor blasting) resolves all three in one automated step. A slurry of water and fine glass bead deburrs, cleans and satin-finishes each instrument to a repeatable 0.25–0.6µm Ra, with no embedded abrasive and every parameter logged for ISO 13485 validation.
Why traditional instrument finishing methods create compliance exposure
Instrument manufacturers regularly use dry blasting, manual polishing, or mass finishing as standalone finishing processes.
vs. dry blasting: The European Hygienic Engineering and Design Group (EHEDG) sets Ra 0.8µm as the maximum for hygienic product-contact surfaces, the most widely cited hygienic surface benchmark. Dry blasting can produce instrument surfaces at Ra 1.3µm or above. That is not a marginal overshoot. It is a surface that is harder to clean and sterilise reliably, and it cannot be validated to a consistent Ra output. Dry blasting also embeds abrasive particles in the substrate. No downstream cleaning step reliably removes them.
vs. manual polishing: Manual polishing introduces operator variability into a process that ISO 13485 requires to be documented, controlled, and validated. Batch-to-batch Ra deviation becomes hard to quantify and control, and difficult to defend under audit. At production volume, the inconsistency compounds.
vs. mass finishing as a standalone step: Mass finishing handles bulk surface smoothing effectively, but cannot deliver the spatial precision that complex instrument profiles require. Box-lock joints, cannulated shafts, serrated jaw faces, and fine hinge pins need controlled, directed media delivery. Mass finishing averages across the geometry. Wet blasting addresses it.
Find out how wet blasting compares with other finishing processes

Wet blasting applications for medical and dental instrument manufacturing
The addition of water cushions media impact, prevents abrasive embedment, eliminates airborne particulate and continuously carries debris away from the surface. The result is a finish that dry processes cannot replicate on a repeatable basis.
Wet blasting with glass beads consistently produces surface roughness between 0.25 and 0.6µm Ra across instrument production runs. That window sits well below EHEDG’s 0.8µm Ra hygienic-surface maximum, leaves fewer surface features for contamination to shelter in during cleaning and autoclave sterilisation, and is consistently achievable in an automated, parameterised process that can be documented for ISO 13485 or FDA QMSR (21 CFR 820) validation.
Wet blasting is applied across the following medical and dental instrument manufacturing operations:
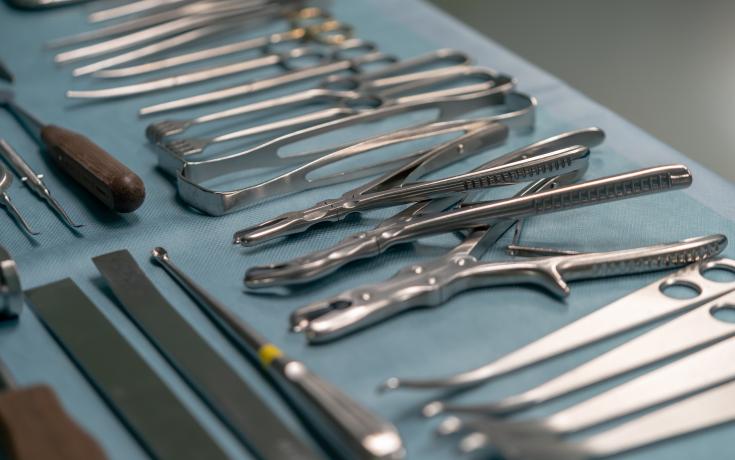
- Deburring and edge radiusing of surgical scissors, clamps, needle holders, bone rongeurs, and retractors
- Non-reflective satin finishing of scalpel handles, probe shafts, and speculum bodies to eliminate operative glare during procedures
- Surface cleaning, descaling, and oxide removal following forging, heat treatment, casting, or welding operations
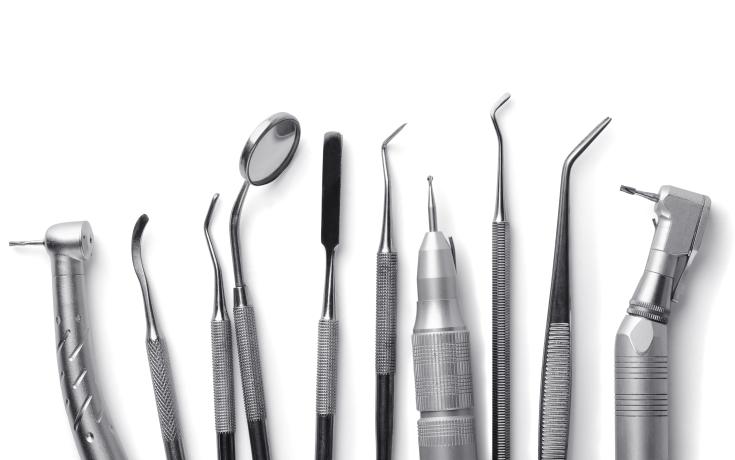
- Deburring, surface smoothing, and sterilisation-surface preparation of dental scalers, curettes, explorers, and periodontal probes
- Finishing of dental rotary instruments including burs, drill heads, and handpiece components
- Surface preparation and post-coating treatment for PVD and DLC application - where wet blasting controls the Ra profile for adhesion prior to coating, and post-coating peening converts tensile to compressive stresses to maximise coating durability
Why Vapormatt
Surgical and dental instrument manufacturers operating within ISO 13485, FDA QMSR (21 CFR 820), or EU MDR supply chains must use a finishing process that is controlled, parameterised, validated, and fully reproducible across every production batch. That makes manual polishing, an operator-dependent process, hard to justify, and creates serious validation challenges for dry blasting, which lacks the process control needed to demonstrate batch-to-batch repeatability. What these regulatory frameworks demand, in practice, is automated machinery capable of delivering quantifiable, auditable output parameters every time.
Vapormatt’s automated machines deliver exactly that. Blast pressure, media concentration, media size, nozzle geometry, slurry conditioning, and cycle duration are all defined, held, and logged. In one trial, a single automatic programme deburred titanium surgical tips in three different geometries to a confirmed visual standard, with micro-geometry intact. Every batch of instruments leaves the machine with the correct finish, free of embedded abrasive, free of heat stress to the substrate, and free of residual particulate contamination.
Most finishing equipment suppliers treat wet blasting as one process among many. Vapormatt's sole focus is wet blasting. That focus, sustained across decades of application engineering, is reflected in a patent portfolio covering process control, slurry conditioning, and media filtration that no generalist finishing company can match.
The bottom line
Surface finishing is where instrument compliance is secured or compromised. Wet blasting at 0.25–0.6µm Ra removes burrs, embedded abrasive and batch-to-batch variation in one automated, documented operation. That is the evidence reviewers expect under ISO 13485, EU MDR and the FDA’s Quality Management System Regulation (QMSR), which brought ISO 13485 into 21 CFR 820 from 2 February 2026.
Related machines




FAQs
What surface roughness do surgical and dental instruments need for reliable sterilisation in an autoclave?
Instrument surfaces should sit well below Ra 0.8µm, the maximum the European Hygienic Engineering and Design Group (EHEDG) sets for hygienic product-contact surfaces and the most widely cited benchmark for cleanable surfaces. Wet blasting with glass beads consistently produces instrument surfaces between 0.25 and 0.6µm Ra. That range leaves fewer surface features for contamination to shelter in during cleaning and autoclaving, and it can be achieved repeatedly across production volume in a validated, automated process.
How does wet blasting satisfy ISO 13485 process validation requirements?
Wet blasting can be validated under ISO 13485 because every parameter that determines the finish is fixed, logged and reproducible. Those parameters are blast pressure, media type, media concentration, nozzle geometry and cycle duration. ISO 13485 requires finishing processes to be controlled, documented and capable of consistent output. Since 2 February 2026, the FDA’s Quality Management System Regulation (QMSR) has incorporated ISO 13485 into 21 CFR 820, so the same validation also supports FDA compliance. Manual polishing and dry blasting produce operator-variable or surface-contaminating outputs that are harder to validate to the same standard.
Will wet blasting damage complex instrument geometry such as serrated jaws, box-lock joints, or fine hinge pins?
No. The water carrier cushions media impact and prevents localised stress on fine geometry. Wet blasting is routinely used on thin-section stainless steel instruments, dental rotary components, and articulating joints without dimensional distortion or substrate damage. Media size and blast pressure are defined per instrument profile during process development, not applied as a generic setting.
What instrument materials can be wet blasted?
Wet blasting is compatible with the full range of materials used in medical and dental instrument manufacture:
- martensitic and precipitation-hardening stainless steels used for cutting and clamping instruments (such as 410, 420, 440A and 17-4PH)
- austenitic grades 304 and 316L
- titanium alloys
- cobalt-chrome
- engineered ceramics
Media selection and process parameters are adjusted per material to deliver the target Ra without altering substrate integrity. Glass bead is non-ferrous, so it introduces no free iron, and instruments can be passivated afterwards as normal.
Can wet blasting replace multiple finishing steps in a single operation?
In many instrument manufacturing workflows, wet blasting consolidates deburring, surface cleaning, scale removal, and sterilisation-surface preparation into a single validated step. Manufacturers currently running sequential deburring, polishing, and cleaning operations typically reduce handling steps, process time, and the number of separate validation activities required under ISO 13485.
Why do surgical instruments have a satin, non-glare finish?
A satin finish scatters light from theatre lamps, so instruments don’t reflect glare at the surgical team. Wet blasting with glass bead gives a uniform satin finish at 0.25–0.6µm Ra, so glare reduction and a cleanable surface come from the same step.
Which Vapormatt machine is best for finishing surgical and dental instruments?
The right machine depends on your production volume and instrument geometry:
- The Sabre five-axis CNC cell suits high-value instruments with complex geometry that need precisely directed blasting.
- The Puma+ automatic machine, available in four configurations, suits smaller component runs and factories that need consistent automated processing.
- The Vapormate compact manual cabinet suits R&D, process development and small-batch finishing.